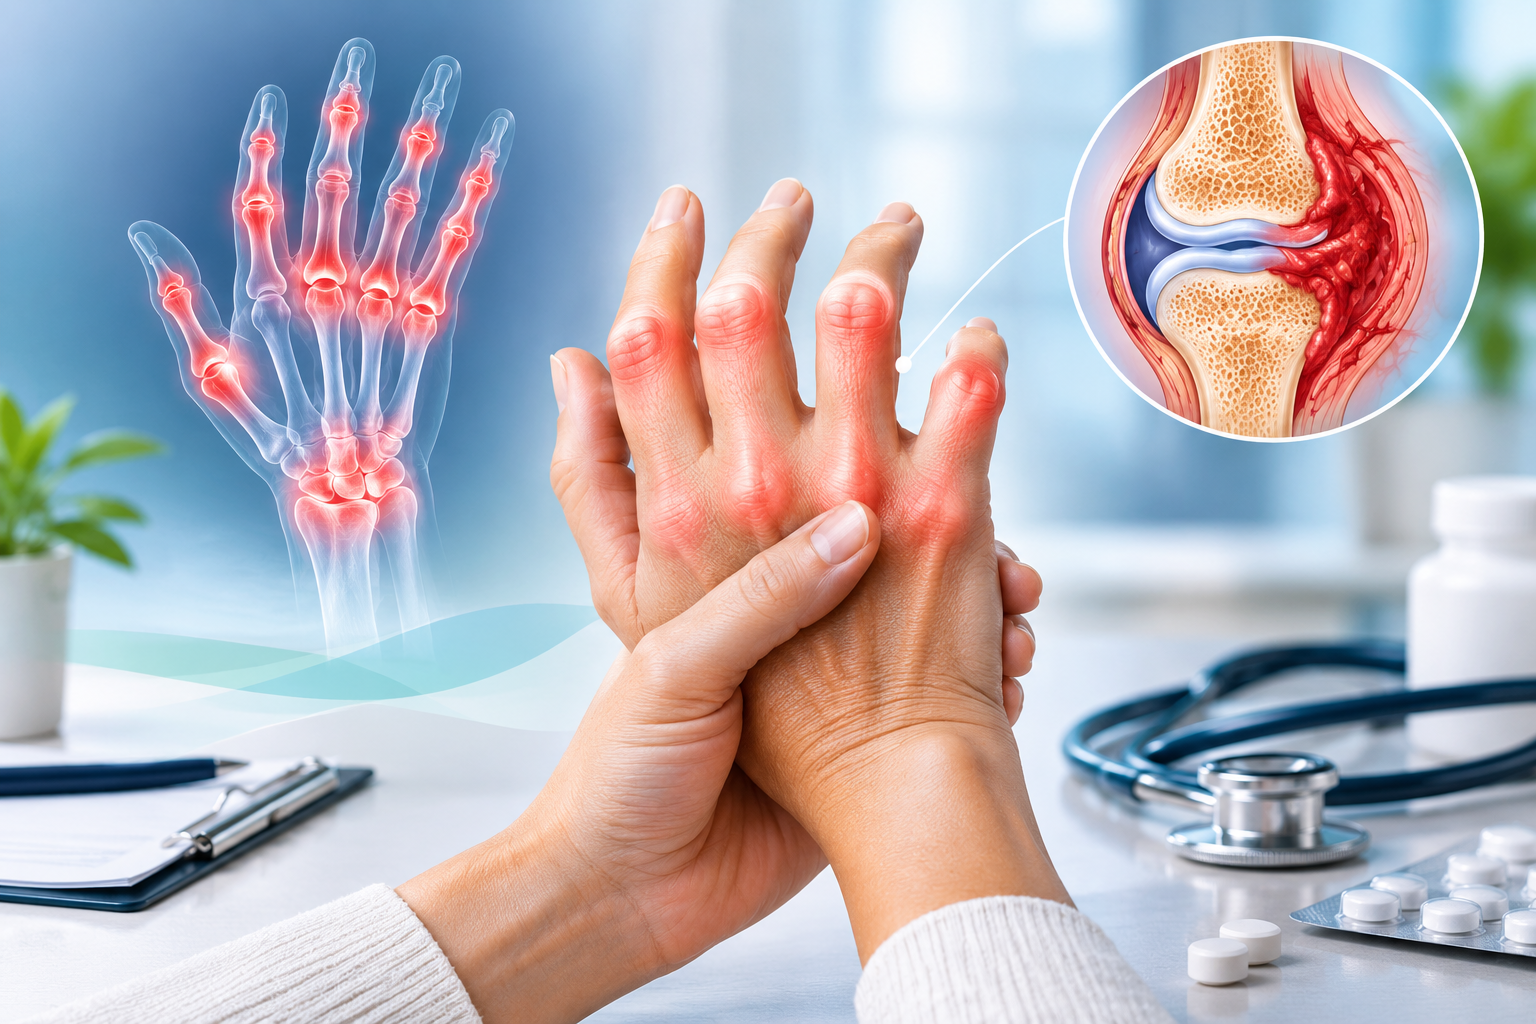
Rheumatoid arthritis (RA) is a chronic autoimmune inflammatory disease that primarily affects the joints but can also affect other organs of the body. Unlike osteoarthritis, which is mainly associated with degeneration and mechanical wear of the joint, rheumatoid arthritis occurs when the immune system mistakenly attacks the body’s own tissues.
The disease mainly affects the synovial membrane of joints, causing persistent inflammation. Over time, uncontrolled inflammation can lead to cartilage destruction, bone erosion, joint deformity, reduced mobility, and disability.
What Is Rheumatoid Arthritis?
Rheumatoid arthritis is a systemic autoimmune disease characterized by persistent inflammation of the synovial joints.
The immune system becomes abnormally activated and produces inflammatory cells and antibodies that attack tissues around the joints.
The inflammatory process can be summarized as:
Autoimmune activation → Synovial inflammation → Synovial thickening → Pannus formation → Cartilage destruction → Bone erosion → Joint deformity
RA can occur at any age, although it commonly develops during adulthood and is more frequently diagnosed in women.
Normal Joint Structure
To understand rheumatoid arthritis, it is helpful to understand the normal joint.
A synovial joint contains:
- Bones
- Articular cartilage
- Synovial membrane
- Synovial fluid
- Joint capsule
- Ligaments
- Tendons and surrounding muscles
The synovial membrane produces synovial fluid, which lubricates the joint and helps reduce friction during movement.
In rheumatoid arthritis, the immune system causes inflammation of this normally thin synovial membrane.
Causes and Risk Factors of Rheumatoid Arthritis
The exact cause of rheumatoid arthritis is not completely understood. It is believed to result from an interaction between genetic susceptibility, immune system abnormalities, and environmental factors.
Important risk factors include:
- Genetic susceptibility
- Family history of rheumatoid arthritis
- Smoking
- Certain environmental exposures
- Female sex
- Obesity and metabolic factors
- Increasing age
Having a risk factor does not necessarily mean that a person will develop rheumatoid arthritis.
Pathophysiology of Rheumatoid Arthritis
The pathophysiology of RA involves a complex interaction between the immune system, inflammatory cells, antibodies, and cytokines.
Step 1: Genetic and Environmental Susceptibility
Some individuals have genetic factors that increase their susceptibility to autoimmune disease.
Environmental factors such as smoking may contribute to abnormal immune activation in genetically susceptible individuals.
Step 2: Abnormal Immune Activation
The immune system becomes activated against the body’s own tissues.
T cells and B cells become involved in the inflammatory response.
B cells can produce characteristic autoantibodies, particularly:
- Rheumatoid factor (RF)
- Anti cyclic citrullinated peptide antibodies (anti CCP or ACPA)
Step 3: Release of Inflammatory Cytokines
Activated immune cells release inflammatory mediators called cytokines.
Important cytokines include:
- Tumor necrosis factor-alpha (TNF-α)
- Interleukin 1 (IL 1)
- Interleukin 6 (IL 6)
These substances promote and maintain inflammation within the joint.
Step 4: Synovitis
The synovial membrane becomes inflamed, producing a condition called synovitis.
The synovium becomes:
- Thickened
- Highly vascular
- Infiltrated with inflammatory cells
This produces joint swelling, warmth, pain, and stiffness.
Step 5: Pannus Formation
Persistent inflammation causes abnormal growth of the synovial tissue.
This abnormal inflammatory tissue is called a pannus.
The pannus grows over the articular cartilage and contributes to progressive joint destruction.
Step 6: Cartilage Destruction
Inflammatory mediators stimulate enzymes that break down articular cartilage.
As cartilage becomes damaged:
Cartilage loss → Increased friction → Pain → Reduced joint movement
Step 7: Bone Erosion
Inflammation stimulates osteoclast activity, resulting in bone resorption.
This produces characteristic marginal bone erosions.
Progressive disease may result in:
- Joint space narrowing
- Bone erosions
- Subluxation
- Joint deformity
- Loss of function
Joints Commonly Affected
Rheumatoid arthritis commonly produces a symmetrical pattern of joint involvement.
Frequently affected joints include:
- Wrist joints
- Metacarpophalangeal (MCP) joints
- Proximal interphalangeal (PIP) joints
- Metatarsophalangeal (MTP) joints
- Knees
- Ankles
- Elbows
- Shoulders
The distal interphalangeal (DIP) joints are usually spared.
Signs and Symptoms of Rheumatoid Arthritis
Joint Pain
Joint pain is one of the most common symptoms. Pain is primarily caused by inflammation of the synovium and surrounding tissues.
Joint Swelling
Inflammation of the synovium and increased joint fluid can cause visible or palpable joint swelling.
Morning Stiffness
A classic feature is prolonged morning stiffness, often lasting more than 30–60 minutes.
The stiffness may improve with gentle movement.
Joint Warmth
Inflammation increases blood flow to the affected joint, producing warmth.
Reduced Range of Motion
Pain, swelling, inflammation, and structural damage can cause limited range of motion.
Fatigue
Because RA is a systemic inflammatory disease, patients may experience significant fatigue and weakness.
Other General Symptoms
Patients may also experience:
- Low grade fever
- Malaise
- Loss of appetite
- Weight loss
- General weakness
Extra Articular Manifestations of Rheumatoid Arthritis
Rheumatoid arthritis is not limited to the joints. It can affect multiple organs.
Skin
Some patients develop rheumatoid nodules, which are firm subcutaneous nodules commonly found around pressure areas such as the elbows.
Eyes
RA may cause:
- Dry eyes
- Episcleritis
- Scleritis
Lungs
Possible pulmonary complications include:
- Interstitial lung disease
- Pleural inflammation
- Pleural effusion
- Pulmonary rheumatoid nodules
Cardiovascular System
RA is associated with increased cardiovascular risk and may cause inflammatory conditions such as pericarditis.
Blood
Patients may develop anemia of chronic inflammation.
Nervous System
Inflammation or joint changes can compress nerves.
For example:
Wrist inflammation → Median nerve compression → Carpal tunnel syndrome
Cervical Spine
An important complication of longstanding rheumatoid arthritis is involvement of the upper cervical spine.
Inflammation around the C1–C2 atlantoaxial joint can cause atlantoaxial instability.
Severe cervical instability can potentially compromise the spinal cord, making cervical assessment important in patients with significant RA.
Rheumatoid Arthritis Hand Deformities
Long standing uncontrolled rheumatoid arthritis can cause characteristic hand deformities.
Ulnar Deviation
The fingers gradually deviate toward the ulnar side of the hand.
Swan-Neck Deformity
Typically involves:
PIP joint hyperextension + DIP joint flexion
Boutonnière Deformity
Typically involves:
PIP joint flexion + DIP joint hyperextension
These deformities can significantly affect hand function and grip strength.
Diagnosis of Rheumatoid Arthritis
There is no single laboratory test that independently confirms rheumatoid arthritis.
Diagnosis is based on:
Clinical history + Physical examination + Laboratory investigations + Imaging
The 2010 ACR/EULAR classification criteria consider:
- Joint involvement
- Serology
- Acute phase reactants
- Duration of symptoms
Laboratory Investigations
Rheumatoid Factor
Rheumatoid factor (RF) is an antibody frequently detected in patients with RA.
However, RF is not completely specific for rheumatoid arthritis and may also occur in other conditions.
Therefore:
Positive RF does not automatically mean rheumatoid arthritis.
Anti CCP Antibody
Anti CCP antibodies, also called ACPA, are highly useful in evaluating suspected RA.
They have relatively high specificity for RA and may be associated with a greater risk of erosive disease.
ESR
Erythrocyte sedimentation rate (ESR) is an inflammatory marker that may be elevated during active disease.
CRP
C-reactive protein (CRP) is another marker of systemic inflammation and can be useful for monitoring disease activity.
Complete Blood Count
A CBC may demonstrate:
- Anemia
- Thrombocytosis associated with inflammation
- Other abnormalities depending on disease or treatment
Imaging in Rheumatoid Arthritis
X-Ray
X rays may show:
- Soft tissue swelling
- Periarticular osteopenia
- Joint space narrowing
- Marginal erosions
- Subluxation
- Deformity
Early rheumatoid arthritis can have normal X rays.
Musculoskeletal Ultrasound
Musculoskeletal ultrasound can detect:
- Synovitis
- Joint effusion
- Increased Doppler vascularity
- Some bone erosions
MRI
MRI is sensitive for detecting:
- Synovitis
- Bone marrow edema
- Early erosions
- Soft tissue abnormalities
Differential Diagnosis
Several conditions can resemble rheumatoid arthritis.
Rheumatoid Arthritis
Typically causes symmetrical inflammatory polyarthritis.
Osteoarthritis
Usually causes degenerative joint disease with pain that is more closely related to activity.
Gout
Often presents with sudden, severe inflammation of a joint, commonly the first metatarsophalangeal joint.
Psoriatic Arthritis
May be associated with:
- Psoriasis
- Nail abnormalities
- Dactylitis
- Asymmetrical arthritis
Systemic Lupus Erythematosus
Can cause inflammatory arthritis but often has other systemic autoimmune manifestations.
Septic Arthritis
A hot, painful, acutely swollen joint with systemic illness may represent septic arthritis, which requires urgent medical evaluation.
Treatment of Rheumatoid Arthritis
The main goals of treatment are to:
- Control inflammation
- Reduce pain
- Prevent joint destruction
- Maintain mobility
- Preserve independence
- Prevent disability
- Achieve remission or low disease activity
Treatment usually requires long-term follow-up with a rheumatologist.
Disease Modifying Antirheumatic Drugs
DMARDs (Disease Modifying Antirheumatic Drugs) are the foundation of rheumatoid arthritis treatment.
Unlike simple painkillers, DMARDs can modify the disease process and reduce the risk of progressive joint damage.
Methotrexate
Methotrexate is commonly used as an initial DMARD when appropriate.
A crucial medication safety point is:
Methotrexate for RA is generally taken once weekly, not daily.
Patients receiving methotrexate require appropriate monitoring, which may include:
- CBC
- Liver function tests
- Renal function
Folic acid is commonly prescribed to reduce certain adverse effects.
Other Conventional DMARDs
Other conventional DMARDs include:
- Hydroxychloroquine
- Sulfasalazine
- Leflunomide
Biologic DMARDs
Patients whose disease remains active despite conventional treatment may require biologic DMARDs.
Examples include:
TNF Inhibitors
- Adalimumab
- Etanercept
- Infliximab
- Certolizumab
- Golimumab
Other Biologic Agents
- Tocilizumab
- Sarilumab
- Abatacept
- Rituximab
The choice of medication depends on factors such as disease activity, previous treatment response, comorbidities, infection risk, and patient-specific considerations.
JAK Inhibitors
JAK inhibitors are targeted synthetic DMARDs.
Examples include:
- Tofacitinib
- Baricitinib
- Upadacitinib
These medications require careful patient selection and monitoring because they can have important risks, including infections and cardiovascular or thrombotic complications in certain patients.
Corticosteroids
Corticosteroids such as prednisone or prednisolone can rapidly reduce inflammation.
They may be used for:
- Severe inflammatory flares
- Short-term bridging therapy
- Certain joint injections
Long-term corticosteroid use is generally minimized because of potential complications such as:
- Osteoporosis
- Hyperglycemia
- Hypertension
- Increased infection risk
- Weight gain
- Cataracts
- Adrenal suppression
NSAIDs
Nonsteroidal anti-inflammatory drugs (NSAIDs) can reduce:
- Pain
- Inflammation
- Stiffness
Examples include:
- Ibuprofen
- Naproxen
- Diclofenac
- Celecoxib
However, NSAIDs do not stop the underlying autoimmune disease or prevent progressive joint destruction.
Potential adverse effects include:
- Gastritis
- Peptic ulcer disease
- Gastrointestinal bleeding
- Kidney injury
- Fluid retention
- Cardiovascular complications
Physical Therapy and Occupational Therapy
Physiotherapy is an important part of RA management.
It can help:
- Maintain range of motion
- Preserve muscle strength
- Reduce stiffness
- Improve mobility
- Prevent contractures
- Improve physical function
Occupational therapy can help patients learn joint protection techniques and use assistive devices when necessary.
Exercise
Appropriate physical activity is generally encouraged.
Useful activities may include:
- Walking
- Swimming
- Cycling
- Range of motion exercises
- Strength training
- Low impact aerobic exercise
During severe disease flares, exercise intensity may need to be modified.
Prolonged complete bed rest should generally be avoided because it can contribute to:
- Muscle wasting
- Joint stiffness
- Reduced cardiovascular fitness
- Functional decline
Surgical Management
Advanced rheumatoid arthritis may require surgery when joint destruction causes severe pain or functional impairment.
Possible procedures include:
- Synovectomy
- Tendon repair
- Joint reconstruction
- Arthrodesis
- Total joint replacement
Joint replacement may be required in severely damaged knees, hips, shoulders, or other joints.
Nursing Assessment of Rheumatoid Arthritis
Nurses play an important role in assessing symptoms, maintaining function, preventing complications, and educating patients.
Pain Assessment
Assess:
- Location
- Severity
- Character
- Duration
- Factors that worsen symptoms
- Factors that relieve symptoms
Joint Assessment
Assess for:
- Swelling
- Warmth
- Tenderness
- Reduced range of motion
- Deformity
- Symmetry
Functional Assessment
Assess the patient’s ability to perform:
- Walking
- Dressing
- Bathing
- Eating
- Writing
- Working
- Other activities of daily living
Neurovascular Assessment
Patients with significant swelling, deformity, surgery, splinting, or casting may require neurovascular assessment.
Remember:
C — Circulation
Assess:
- Skin color
- Temperature
- Capillary refill
- Peripheral pulses
M — Motor
Assess:
- Ability to move the affected extremity
S —Sensory
Assess:
- Numbness
- Tingling
- Altered sensation
Any acute deterioration should be reported promptly.
Nursing Interventions
Pain Management
Nursing interventions include:
- Assessing pain regularly
- Administering prescribed medications
- Evaluating medication effectiveness
- Using appropriate non pharmacological measures
- Supporting comfortable positioning
Mobility Management
Encourage appropriate:
- Range of motion exercises
- Ambulation
- Strengthening exercises
- Physiotherapy
Assistive devices may be used when necessary.
Joint Protection
Teach patients to:
- Avoid excessive stress on affected joints
- Avoid prolonged repetitive movements
- Use appropriate assistive equipment
- Balance activity with rest
- Use larger joints when appropriate for certain tasks
Fatigue Management
Fatigue is common in rheumatoid arthritis.
Patients should be encouraged to use:
Plan → Prioritize → Perform → Rest
Energy conservation techniques can help patients maintain independence while reducing excessive fatigue.
Medication Monitoring
Patients receiving DMARDs, biologic medications, JAK inhibitors, or corticosteroids require appropriate monitoring.
Nurses should monitor:
- Medication adherence
- Adverse effects
- Signs of infection
- Laboratory results
- Disease activity
- Vaccination status
- Drug interactions
Depending on the medication, screening for infections such as tuberculosis and hepatitis B/C may be required before treatment.
Infection Prevention
Some RA medications modify or suppress immune responses.
Patients should be educated to report symptoms such as:
- Fever
- Persistent cough
- Shortness of breath
- Unusual wounds
- Urinary symptoms
- Persistent diarrhea
- Other signs of infection
A new infection should not automatically be assumed to be an RA flare.
Patient Education
Patients should understand that rheumatoid arthritis is a chronic condition that can often be controlled effectively with appropriate treatment.
Important education includes:
- Take medications exactly as prescribed.
- Do not stop DMARDs without medical advice.
- Attend regular follow up appointments.
- Report medication side effects.
- Report signs of infection.
- Maintain appropriate physical activity.
- Protect affected joints.
- Avoid smoking.
- Maintain a healthy weight and balanced diet.
Diet and Lifestyle
There is no specific diet that cures rheumatoid arthritis.
However, a healthy dietary pattern can support general health.
A balanced diet may include:
- Vegetables
- Fruits
- Whole grains
- Adequate protein
- Healthy fats
- Fish and other sources of omega 3 fatty acids
Patients should also maintain appropriate calcium and vitamin D intake according to their individual needs.
Smoking and Rheumatoid Arthritis
Smoking is an important modifiable risk factor.
Smoking is associated with:
- Increased risk of RA
- More severe disease in some patients
- Reduced treatment response
- Increased cardiovascular risk
- Increased respiratory complications
Smoking cessation is therefore an important component of comprehensive RA care.
Complications of Rheumatoid Arthritis
Poorly controlled or longstanding RA can result in:
Joint Complications
- Cartilage destruction
- Bone erosion
- Joint deformity
- Subluxation
- Contractures
- Reduced mobility
- Functional disability
Systemic Complications
- Cardiovascular disease
- Interstitial lung disease
- Osteoporosis
- Anemia
- Eye inflammation
- Nerve compression
- Cervical spine instability
Rheumatoid Arthritis vs Osteoarthritis
| Feature | Rheumatoid Arthritis | Osteoarthritis |
|---|---|---|
| Main mechanism | Autoimmune inflammation | Degenerative/mechanical changes |
| Synovitis | Common | Usually less prominent |
| Joint pattern | Often symmetrical | Variable |
| Morning stiffness | Often prolonged | Usually shorter |
| MCP/PIP involvement | Common | Less typical |
| DIP involvement | Usually spared | Common |
| Systemic symptoms | May occur | Usually absent |
| RF/Anti-CCP | May be positive | Not characteristic |
| Bone erosions | Can occur | Not typical RA-type erosions |
| Main treatment concept | DMARDs + symptom control | Exercise, symptom control, and surgery when indicated |

Rheumatoid Arthritis: Important Points to Remember
For nursing students and healthcare professionals, remember these key points:
- Rheumatoid arthritis is an autoimmune inflammatory disease.
- It primarily affects the synovial membrane.
- RA commonly causes symmetrical polyarthritis.
- The MCP, PIP, and wrist joints are commonly affected.
- The DIP joints are usually spared.
- Morning stiffness lasting more than 30–60 minutes is characteristic of inflammatory arthritis.
- RF and anti-CCP are important serological markers.
- DMARDs are used to modify the disease and reduce progression.
- NSAIDs mainly provide symptomatic relief and do not prevent joint destruction.
- Longstanding disease may cause ulnar deviation, swan-neck deformity, and boutonnière deformity.
- RA can affect organs outside the joints, including the lungs, cardiovascular system, eyes, blood, and cervical spine.
- Early diagnosis and appropriate treatment can help reduce joint damage and preserve function.
© 2026 Amina Rehman — aminarehman.com


Leave a Reply