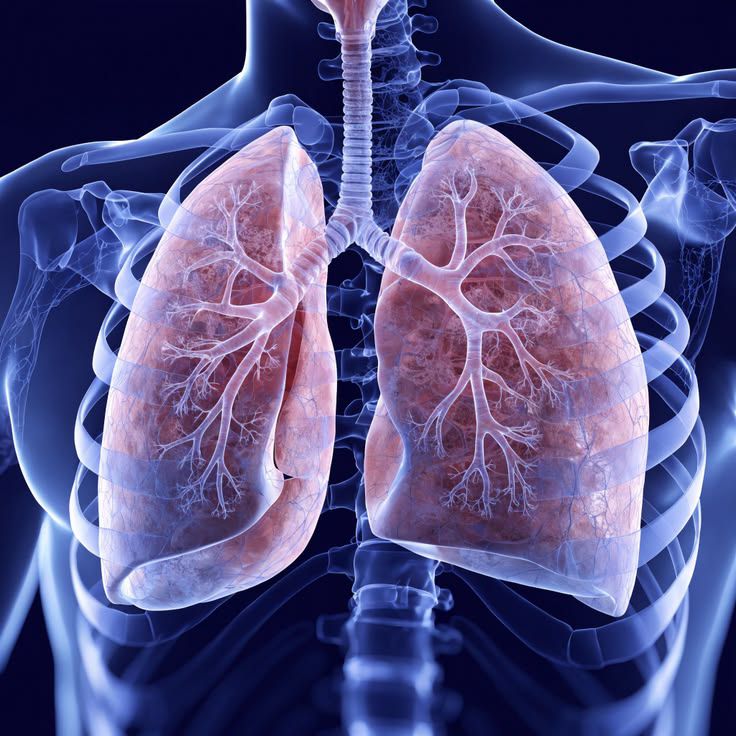
Bronchiectasis is a long term condition of the lungs in which the airways become permanently widened and damaged. These damaged airways have difficulty removing mucus effectively. As mucus remains trapped inside the lungs, bacteria can grow more easily, which may lead to repeated infections and inflammation.
People with bronchiectasis may have a persistent cough, excessive phlegm, recurrent chest infections, shortness of breath, wheezing, tiredness, and sometimes blood in the sputum. Some people have mild disease and experience occasional symptoms, while others may have frequent flare ups that significantly affect daily life.
Although the structural changes in the airways usually cannot be completely reversed, proper treatment can help control symptoms, reduce infections, improve breathing, and protect lung function.
Medical disclaimer: This article is intended for general educational purposes. It does not replace a medical examination, diagnosis, or personalized treatment from a qualified healthcare professional.
What Is Bronchiectasis?
Bronchiectasis occurs when the bronchi, which are the larger tubes that carry air into and out of the lungs, become permanently widened and damaged.
The lungs normally produce mucus to trap dust, particles, and microorganisms. Tiny hair like structures called cilia then help move the mucus toward the throat, where it can be swallowed or coughed out.
In bronchiectasis, this natural cleaning system does not work properly. Damaged airways allow mucus to collect inside them. Bacteria can remain in this mucus and cause repeated inflammation.
This creates an ongoing cycle in which airway damage leads to mucus retention, mucus retention encourages infection, infection causes inflammation, and inflammation can contribute to further airway damage.
Understanding this cycle is important because bronchiectasis treatment is not simply about treating infections. Improving mucus clearance and addressing the underlying cause are also important parts of management.

What Causes Bronchiectasis?
There is no single cause of bronchiectasis. A number of different diseases and conditions can damage the airways and eventually lead to bronchiectasis.
Sometimes doctors can identify a clear cause. In other people, extensive testing does not reveal a specific reason.
Previous Lung Infections
Serious or repeated lung infections can damage the airways.
Previous pneumonia, tuberculosis, whooping cough, measles, and other severe respiratory infections may sometimes contribute to the development of bronchiectasis.
The risk depends on factors such as the severity of the infection and the individual’s immune response.
Immune System Problems
The immune system helps protect the lungs from infections. People with certain immune deficiencies may experience repeated respiratory infections.
Repeated infections can gradually damage the airways and contribute to bronchiectasis.
For this reason, doctors may investigate immune function when someone is newly diagnosed with bronchiectasis.
Cystic Fibrosis
Cystic fibrosis is an inherited condition that can cause thick mucus and recurrent lung infections.
Bronchiectasis is an important feature of cystic fibrosis, although cystic fibrosis related bronchiectasis is managed somewhat differently from other forms of bronchiectasis.
Primary Ciliary Dyskinesia
Primary ciliary dyskinesia is a rare genetic condition in which the tiny cilia that help move mucus do not function normally.
Poor mucus clearance can lead to repeated respiratory infections and eventually airway damage.
Asthma and COPD
Some people with asthma or chronic obstructive pulmonary disease, commonly known as COPD, may also have bronchiectasis.
Having more than one respiratory condition can make symptoms more complicated and may influence the treatment plan.
Allergic Bronchopulmonary Aspergillosis
Allergic bronchopulmonary aspergillosis, or ABPA, is an allergic reaction to fungi such as Aspergillus.
It is particularly associated with asthma and can cause airway inflammation and bronchiectasis.
Because ABPA has specific treatment options, identifying it can be important.
Autoimmune Diseases
Certain autoimmune and inflammatory diseases can be associated with bronchiectasis.
Examples include rheumatoid arthritis and Sjögren syndrome.
In these situations, controlling the underlying disease may form part of the overall respiratory management plan.
Aspiration
Repeated aspiration occurs when food, stomach contents, liquids, or saliva enter the airways instead of going safely into the digestive system.
Repeated aspiration can irritate and damage the lungs and may contribute to bronchiectasis.
Nontuberculous Mycobacteria
Nontuberculous mycobacteria, often abbreviated as NTM, are bacteria found naturally in the environment.
Certain NTM species can cause lung disease, particularly in people who already have structural abnormalities in their lungs.
Doctors may therefore perform specialized sputum testing when NTM infection is suspected.
Sometimes the Cause Remains Unknown
Even after appropriate testing, the cause of bronchiectasis cannot always be identified.
This is sometimes referred to as idiopathic bronchiectasis.
Not finding an underlying cause does not mean that the condition cannot be treated. Treatment can still focus on mucus clearance, infection control, prevention of flare ups, exercise, and maintaining good lung function.

How Does Bronchiectasis Develop?
The development of bronchiectasis can be understood as a continuing cycle.
An infection or another inflammatory process may initially injure the airways. The damaged airway walls then become permanently widened.
Because the airways are no longer normal, mucus becomes harder to remove. Retained mucus provides an environment where bacteria can remain.
The immune system responds to these organisms, producing inflammation. Repeated inflammation can cause additional airway damage.
Over time, this may result in more mucus, more infections, and worsening respiratory symptoms.
This is why breaking the cycle of mucus retention and repeated infection is one of the major goals of bronchiectasis treatment.
What Are the Symptoms of Bronchiectasis?
The symptoms of bronchiectasis vary from one person to another.
The most characteristic symptom is a long lasting cough, often accompanied by mucus or sputum.
Some people cough throughout the day, while others notice more coughing in the morning when mucus has accumulated overnight.
Other common symptoms include shortness of breath, wheezing, fatigue, recurrent chest infections, chest discomfort, and coughing up blood.
Persistent Cough
A chronic cough is one of the most common signs of bronchiectasis.
The cough may be dry in some individuals, but many people produce sputum when they cough.
A persistent productive cough should not simply be dismissed as a normal feature of aging or repeated minor infections. It deserves medical assessment, particularly when it continues for weeks or months.
Excessive Phlegm
People with bronchiectasis may produce considerable amounts of mucus.
The sputum may appear clear, white, yellow, green, or another color.
The appearance of mucus can change during an infection or flare up, but sputum color by itself does not determine whether antibiotics are necessary.
Shortness of Breath
Breathlessness can occur because of airway obstruction, mucus accumulation, infection, reduced lung function, or other associated lung diseases.
Some people notice breathlessness mainly when walking quickly, climbing stairs, or exercising.
Wheezing
Some people with bronchiectasis experience wheezing, particularly when they also have asthma or airway obstruction.
Fatigue
Chronic coughing, recurrent infections, disturbed sleep, inflammation, and the increased effort involved in breathing can all contribute to persistent tiredness.

Coughing Up Blood
Hemoptysis, which means coughing up blood, can occur in bronchiectasis.
The amount may range from small streaks of blood in sputum to more significant bleeding.
Any unexplained or recurrent blood in the sputum should be medically assessed. Heavy bleeding requires urgent medical attention.
What Is a Bronchiectasis Flare Up?
A bronchiectasis exacerbation, commonly called a flare up, occurs when respiratory symptoms become noticeably worse than the person’s usual condition.
Someone may suddenly develop more coughing, increased sputum production, thicker mucus, worsening breathlessness, greater fatigue, fever, chest discomfort, or a change in the usual pattern of their symptoms.
Some patients experience only occasional flare ups, while others may have several each year.
Frequent exacerbations are important because they can significantly affect quality of life and may contribute to further deterioration.
What Can Trigger a Bronchiectasis Flare Up?
Respiratory infections are an important trigger.
Other factors may include changes in bacteria living in the airways, difficulty clearing mucus, exposure to cigarette smoke, air pollution, and other illnesses.
Sometimes a clear trigger cannot be identified.
Learning to recognize changes from your normal symptoms can help you seek medical advice earlier.
How Is Bronchiectasis Diagnosed?
A diagnosis of bronchiectasis is based on a combination of symptoms, imaging, lung function assessment, sputum testing, and investigation of possible underlying causes.
Medical History
A doctor may ask about your cough, sputum production, previous chest infections, pneumonia, tuberculosis, childhood illnesses, asthma, COPD, autoimmune disease, digestive problems, medications, smoking exposure, and family history.
This information can help identify both bronchiectasis and its possible cause.
Physical Examination
During an examination, a healthcare professional may listen to the lungs with a stethoscope.
Some patients have abnormal sounds such as crackles or wheezing.
However, physical examination alone cannot confirm bronchiectasis.
Chest X Ray
A chest X ray may provide useful information and can help doctors investigate other causes of respiratory symptoms.
However, a normal chest X ray does not always rule out bronchiectasis.
CT Scan
A CT scan of the chest is particularly important for diagnosing bronchiectasis.
It can show abnormal widening of the airways and other structural changes that may not be visible on a standard chest X ray.
A CT scan can also help doctors understand how extensive the disease is and which areas of the lungs are affected.
Sputum Testing
Sputum culture can identify bacteria and other organisms present in the respiratory tract.
This is particularly useful in people who have recurrent infections.
Testing may identify organisms such as Pseudomonas aeruginosa or nontuberculous mycobacteria.
Knowing which organisms are present can help doctors make appropriate treatment decisions.
Blood Tests
Blood tests may be performed to investigate possible causes.
Depending on the individual situation, doctors may assess immune function, allergic conditions, inflammation, or other diseases associated with bronchiectasis.
Lung Function Tests
Pulmonary function tests, particularly spirometry, measure how effectively the lungs move air.
These tests can help determine whether airflow obstruction or reduced lung function is present.
They can also help doctors monitor respiratory function over time.
Bronchoscopy
In selected cases, doctors may recommend bronchoscopy.
During bronchoscopy, a thin flexible camera is passed into the airways.
The procedure can help doctors examine the bronchial tubes, collect samples, or investigate a possible blockage or foreign body.
Bronchoscopy is not necessary for everyone with bronchiectasis.
Why Is Finding the Cause Important?
Identifying the underlying cause of bronchiectasis is an important part of good medical care.
Some causes have specific treatments.
For example, identifying immune deficiency, allergic bronchopulmonary aspergillosis, cystic fibrosis, primary ciliary dyskinesia, autoimmune disease, or certain infections may significantly influence treatment.
For this reason, a diagnosis of bronchiectasis should ideally be followed by an appropriate evaluation rather than simply treating symptoms indefinitely.
Treatment of Bronchiectasis
There is no single treatment that works for every person with bronchiectasis.
Treatment is individualized according to symptoms, lung function, infection history, exacerbation frequency, underlying cause, age, other medical conditions, and previous test results.
The main goals are to clear mucus, reduce infections, prevent flare ups, improve breathing, maintain physical activity, and preserve quality of life.
Airway Clearance
Airway clearance is one of the most important parts of bronchiectasis management.
Respiratory physiotherapists can teach patients techniques that help move mucus from the smaller airways toward the larger airways, making it easier to cough out.
Techniques may include controlled breathing, huff coughing, postural drainage, positive expiratory pressure devices, and other specialized methods.
The best technique depends on the individual patient.
Regular airway clearance can help reduce mucus accumulation and may make daily breathing more comfortable.
Hydration and Mucus Management
Drinking an appropriate amount of fluid can help some people keep respiratory secretions easier to clear.
Some patients may also benefit from mucoactive treatments or inhaled saline.
These treatments should be discussed with a healthcare professional because they are not appropriate in exactly the same way for everyone.
Antibiotics
Antibiotics may be prescribed when a bacterial infection or exacerbation is suspected.
The choice of antibiotic can depend on previous sputum cultures, known bacterial resistance, allergies, previous treatments, and the severity of symptoms.
Antibiotics should not be taken unnecessarily or saved from an old prescription.
Using antibiotics incorrectly can cause side effects and contributes to antibiotic resistance.
Long Term Antibiotic Treatment
Some people with frequent exacerbations may benefit from long term antibiotic treatment.
For selected patients, doctors may consider treatments such as macrolide antibiotics or inhaled antibiotics.
These medicines require careful medical supervision because doctors need to consider potential side effects, drug interactions, resistance, heart rhythm problems, hearing effects, and the possibility of nontuberculous mycobacterial infection.
Long term antibiotics are not appropriate for everyone with bronchiectasis.
Inhalers and Bronchodilators
Some people with bronchiectasis also have asthma, COPD, or significant airflow obstruction.
In these circumstances, bronchodilator inhalers may be useful.
However, bronchiectasis itself does not automatically mean that a person needs an inhaler.
Treatment should be based on the patient’s specific respiratory condition.
Inhaled Steroids
Inhaled corticosteroids are not routinely required for everyone with bronchiectasis.
They may be appropriate when a person also has asthma or another condition for which inhaled corticosteroids are recommended.
Using them without a clear medical indication is not generally advised.
Pulmonary Rehabilitation
Pulmonary rehabilitation combines exercise training, education, and strategies for managing breathing problems.
It may be particularly useful for people who have significant breathlessness or reduced exercise capacity.
Regular supervised exercise can help improve physical fitness, muscle strength, endurance, and confidence with activity.
Newer Treatments
Treatment for bronchiectasis continues to develop.
One newer medicine is brensocatib, which targets inflammatory pathways involved in neutrophil activity. It has emerged as a treatment option for selected adults with non cystic fibrosis bronchiectasis in countries and clinical situations where it is approved and appropriate.
Availability and eligibility differ between countries, so patients should discuss newer treatments with a respiratory specialist.
Surgery
Most people with bronchiectasis do not need surgery.
In selected patients, surgery may be considered when severe disease is limited to a particular area of the lung, symptoms remain uncontrolled despite appropriate treatment, or significant recurrent bleeding occurs.
Surgery requires careful specialist assessment.
Oxygen Therapy
Some people with advanced lung disease develop persistently low oxygen levels.
In such situations, oxygen therapy may be prescribed after appropriate testing.
Oxygen should not be started simply because someone feels short of breath. The need for oxygen should be determined by a healthcare professional using clinical assessment and oxygen measurements.
Can Bronchiectasis Be Cured?
In most cases, the structural airway damage caused by bronchiectasis cannot be completely reversed.
However, this does not mean that people with bronchiectasis cannot live active and fulfilling lives.
Many patients can control their symptoms and reduce the frequency of infections through regular airway clearance, appropriate treatment, exercise, vaccination, smoking cessation, and management of the underlying cause.
The aim is to prevent the cycle of mucus accumulation, infection, inflammation, and further airway damage.
Bronchiectasis and Diet
There is no special food or diet that can cure bronchiectasis.
However, good nutrition is important for people with chronic respiratory disease.
A balanced diet containing adequate protein, vegetables, fruits, whole grains, healthy fats, and sufficient fluids can support general health.
Some people with severe respiratory disease lose weight or struggle with appetite.
Anyone experiencing unexplained weight loss should discuss it with a healthcare professional.
A dietitian may be helpful when nutritional needs are difficult to meet.
Exercise and Bronchiectasis
Regular physical activity can be beneficial for people with bronchiectasis.
Exercise can improve fitness, muscle strength, endurance, and overall quality of life.
It may also reduce the physical deconditioning that can occur when people become afraid to exercise because of breathlessness.
The appropriate level of activity depends on the person’s health.
Anyone with severe breathlessness, significant heart disease, low oxygen levels, chest pain, or unstable respiratory symptoms should seek professional advice before starting a new exercise program.
Smoking and Bronchiectasis
Smoking is harmful to damaged airways and can make respiratory symptoms worse.
If you have bronchiectasis and smoke, quitting is one of the most important steps you can take to protect your lungs.
It is also sensible to avoid secondhand smoke and unnecessary exposure to strong chemical fumes and polluted air.
Vaccination and Infection Prevention
Respiratory infections can cause serious flare ups in people with bronchiectasis.
Keeping vaccinations up to date may help reduce the risk of certain preventable infections.
Depending on age, health conditions, and local recommendations, vaccination may include protection against influenza, COVID 19, and pneumococcal disease.
Good hand hygiene and avoiding close contact with people who have contagious respiratory infections can also help reduce exposure.
Vaccination recommendations differ between countries, so it is best to follow local medical advice.
Bronchiectasis and Tuberculosis
A previous episode of pulmonary tuberculosis can cause permanent damage to lung tissue and airways.
This damage may contribute to bronchiectasis.
However, having bronchiectasis does not mean that someone currently has tuberculosis.
If a person develops symptoms such as persistent cough, fever, night sweats, unexplained weight loss, or coughing up blood, a doctor may investigate tuberculosis and other possible causes depending on the person’s medical and exposure history.
Bronchiectasis and Pseudomonas
Pseudomonas aeruginosa is an important bacterium in bronchiectasis.
Some patients develop persistent infection or colonization with this organism.
Its presence can influence the risk of future exacerbations and may affect antibiotic choices.
For this reason, regular sputum testing can be an important part of ongoing care for people who produce sputum.
Possible Complications of Bronchiectasis
Bronchiectasis can range from mild to severe.
Some people experience only occasional symptoms, while others develop complications that require ongoing specialist care.
Recurrent Chest Infections
Repeated respiratory infections are common in bronchiectasis.
These infections may require antibiotics and sometimes hospital treatment.
Frequent Exacerbations
Repeated flare ups can interfere with work, education, sleep, exercise, and everyday activities.
They may also contribute to a decline in lung function in some patients.
Coughing Up Blood
Hemoptysis is another possible complication.
Small amounts of blood may occur, but heavy bleeding can be dangerous and requires urgent medical care.
Reduced Exercise Capacity
Chronic breathlessness and fatigue can make physical activity difficult.
Over time, avoiding activity may cause muscle weakness and physical deconditioning.
Respiratory Failure
In advanced cases, severe lung disease may interfere with the body’s ability to maintain adequate oxygen levels or remove carbon dioxide.
Pulmonary Hypertension
Severe chronic lung disease can sometimes contribute to pulmonary hypertension, which means increased pressure in the blood vessels supplying the lungs.
Poor Nutrition
Persistent illness, increased breathing effort, reduced appetite, and repeated infections may contribute to weight loss and nutritional problems.
When Is Bronchiectasis an Emergency?
Seek urgent medical help if you experience severe difficulty breathing, severe chest pain, confusion, bluish lips or skin, or significant coughing of blood.
Heavy bleeding from the airways can be dangerous.
A sudden major deterioration in breathing or oxygen levels should also be treated as an emergency.
When Should You See a Doctor?
You should consider medical evaluation if you have a cough that continues for several weeks, frequent chest infections, daily mucus production, unexplained breathlessness, recurrent wheezing, coughing up blood, unexplained weight loss, or persistent fatigue.
People who have previously experienced severe lung infections or tuberculosis may also benefit from discussing persistent respiratory symptoms with a healthcare professional.
Early assessment can help identify bronchiectasis and determine whether there is an underlying condition that can be specifically treated.
Living With Bronchiectasis
Living with bronchiectasis often becomes easier when patients understand their own symptoms and develop a consistent management routine.
Pay attention to your normal amount and appearance of sputum. A sudden change can sometimes be an early sign of an exacerbation.
Follow the airway clearance routine recommended by your healthcare professional.
Take prescribed medicines as directed and discuss side effects rather than stopping treatment independently.
Try to remain physically active within your own ability.
Avoid smoking and keep recommended vaccinations up to date.
Regular follow up is also important because bronchiectasis can change over time.
Does Bronchiectasis Get Worse Over Time?
There is no single pattern for everyone.
Some people remain stable for many years, while others experience frequent exacerbations and gradual deterioration.
Several factors can influence the outlook, including lung function, frequency of exacerbations, chronic bacterial infection, underlying cause, extent of airway damage, other medical conditions, and treatment adherence.
This is why modern bronchiectasis care looks at the entire patient rather than relying only on the appearance of a CT scan.
Bronchiectasis vs Bronchitis
The names sound similar, but bronchiectasis and bronchitis are different conditions.
Bronchitis generally refers to inflammation of the bronchial tubes and is often associated with an acute respiratory infection.
Bronchiectasis involves permanent structural widening and damage of the airways.
A person can experience bronchitis while also having bronchiectasis, but one condition should not automatically be assumed to mean the other.
Bronchiectasis vs COPD
COPD is a chronic lung disease characterized by persistent airflow limitation and is commonly associated with smoking and other long term exposures.
Bronchiectasis is primarily characterized by permanent widening of the airways and impaired mucus clearance.
Some people have both conditions.
When bronchiectasis and COPD occur together, symptoms and treatment can become more complex.
Bronchiectasis vs Asthma
Asthma involves inflammation and variable narrowing of the airways.
Bronchiectasis involves permanent structural airway changes.
Both conditions can occur in the same person.
If someone with asthma has a persistent productive cough, recurrent infections, or significant daily sputum, further investigation may be appropriate.
Frequently Asked Questions About Bronchiectasis
Is bronchiectasis contagious?
Bronchiectasis itself is not contagious.
However, some infections that occur in people with bronchiectasis can be contagious. The specific infection determines whether transmission is possible.
Is bronchiectasis permanent?
The structural widening of the airways is generally permanent.
However, symptoms and exacerbations can often be controlled with appropriate treatment.
Can bronchiectasis be completely cured?
Established structural airway damage usually cannot be completely reversed.
However, proper management can reduce symptoms, lower the risk of infections, and improve quality of life.
Can bronchiectasis cause a daily cough?
Yes. A chronic productive cough is one of the most common symptoms.
Is mucus always present?
No.
Some people produce large amounts of sputum, while others have relatively little mucus.
What color can bronchiectasis sputum be?
Sputum may be clear, white, yellow, green, or another color.
Color alone cannot determine whether a person has a bacterial infection or whether antibiotics are necessary.
Can bronchiectasis cause shortness of breath?
Yes.
Shortness of breath can occur because of mucus accumulation, airway obstruction, infection, reduced lung function, or associated diseases.
Can bronchiectasis cause blood in sputum?
Yes.
Coughing up blood can occur because of changes in the blood vessels around damaged airways.
New, recurrent, or significant bleeding should be medically assessed.
Can people with bronchiectasis exercise?
Yes.
For most appropriately assessed patients, regular physical activity is beneficial.
The type and intensity should be adapted to individual health and exercise capacity.
Does everyone with bronchiectasis need antibiotics?
No.
Antibiotics are used when they are medically appropriate. Some patients with frequent exacerbations may require longer term antibiotic strategies, but this is decided individually.
Does everyone with bronchiectasis need an inhaler?
No.
Inhalers are generally prescribed when there is an appropriate reason, such as asthma, COPD, or significant airflow obstruction.
Can bronchiectasis affect both lungs?
Yes.
Bronchiectasis may affect one localized area or several regions of one or both lungs.
Can tuberculosis cause bronchiectasis?
Yes.
Previous pulmonary tuberculosis can leave permanent lung and airway damage that may contribute to bronchiectasis.
Can children develop bronchiectasis?
Yes.
Bronchiectasis can occur in children, although the causes, investigations, and treatment approach may differ from those used in adults.
Bronchiectasis is a chronic lung condition involving permanent widening and damage of the airways.
The condition often causes a persistent cough and mucus production.
Repeated chest infections are common.
A number of conditions can contribute to bronchiectasis, including previous serious infections, immune problems, cystic fibrosis, primary ciliary dyskinesia, autoimmune diseases, ABPA, aspiration, and certain bacterial infections.
A CT scan of the chest is an important investigation for confirming the structural changes associated with bronchiectasis.
Sputum testing can identify bacteria and other organisms that may influence treatment.
Doctors should investigate potentially treatable underlying causes.
Airway clearance is one of the most important parts of long term management.
Antibiotics may be needed for bacterial infections and selected patients may benefit from longer term antibiotic treatment.
Exercise and pulmonary rehabilitation can help people with reduced physical capacity.
Smoking cessation and appropriate vaccination can help protect respiratory health.
Copyright
© 2026 Amina Rehman. All Rights Reserved.
This article has been written as original content for aminarehman.com. It is not copied from another website and should not be reproduced, republished, or redistributed in full without permission.


Leave a Reply